Top Reasons Medicare Claims Get Denied at Independent Practices
Structural problems in patient registration and prior authorization drive most Medicare denials.

Medicare claim denials at independent practices have become a predictable, structural problem rather than a scattering of clerical mistakes. The pattern runs from the front desk through coding to the clinical note itself, and each stage fails in its own specific way.
Medicare denial rates at independent practices are rising steadily
Independent practices are operating in a denial environment that looks nothing like it did two years ago, and the shift has little to do with staff competence. Medicare Advantage plans now deny roughly twice the share of claims that traditional fee-for-service Medicare denies, and the rate at which MA plans turn down prior authorization requests has climbed year after year. Industry analysts describe the current environment as a "perfect storm": new AI-driven payer review systems, a major restructuring of the Medicare Advantage market, and tightening coding requirements all arriving simultaneously.
The cost of fighting back falls almost entirely on the practice. Staff hours and money go toward overturning denials that, by the numbers, should never have been issued. That financial drag matters because it is not evenly distributed across the industry: it concentrates on practices too small to run a dedicated appeals operation, and it recurs with enough regularity that the causes can be sorted into a handful of repeatable failure points. The rest of this piece works through them in the order they actually occur, from the moment a patient checks in to the moment a payer's algorithm reads the chart.
Eligibility errors and plan-transition chaos generate denials before a claim is ever coded
Denials often begin before anyone has written a code. A large share of them trace back to patient registration, where front-desk staff accept coverage information that is outdated or simply unverified, and the 2026 Medicare Advantage enrollment disruption has made that risk far worse than it used to be. A 2025 survey found missing or inaccurate claim data to be the single biggest driver of denials, with registration errors such as wrong demographics or missing insurance information close behind, and both problems grew compared to the year before.
The 2026 restructuring of the MA market is the backdrop that makes this so damaging. Picture a patient who shows up carrying a UnitedHealthcare PPO card, genuinely unaware that the plan has changed to an Aetna HMO. If the front desk doesn't check coverage in real time, the claim goes out to the wrong payer and bounces back, and by the time staff sort out who the correct payer actually is, the window for securing an HMO referral may already have closed. None of that is the patient's fault. The plan changed around them, often without a clear explanation of what the change required.
That PPO-to-HMO shift creates a second, separate trap. HMOs now make up 57% of all Medicare Advantage plans for 2026, a sharp jump as carriers moved people into HMOs to hold premiums down. HMOs require a referral from the primary care physician before a specialist visit happens, and a specialist who sees an HMO patient without that referral on file will have the claim denied with no path to appeal, because the requirement itself was never met. Many patients don't even know the rule applies to them: the broker agents who moved them from a PPO to an HMO frequently skipped over the access rules entirely. A prior authorization secured under the old plan doesn't carry over to the new one either, so a patient already mid-treatment when their plan changed on January 1 has to start the authorization process from scratch, and anything billed during that gap gets denied.
The fix is not complicated in concept, even if it takes discipline to run consistently: verify eligibility in real time at every visit, for every Medicare patient, rather than relying on periodic checks or the assumption that a returning patient's coverage hasn't changed. Some practices are starting to hand this task to computer-use agents that log into payer portals at the moment of the appointment, pull current coverage and referral status, and flag any mismatch before the patient is seen, without requiring a single change to the EHR or practice management system already in place. The deeper implications of that kind of automation, and where it fits against the prior authorization burden described next, matter more the further a claim travels through the system.
How prior authorization requirements (especially under Medicare Advantage) become a systematic revenue drain
Prior authorization denial is the single most common reason a Medicare Advantage claim doesn't get paid, and the sheer scale of managing it has outgrown what independent practice staff can reasonably keep up with. MA plans processed close to 53 million prior authorization determinations in 2024 alone, and the share of those requests getting denied has climbed steadily since.
Part of the reason denial rates run so high is a mismatch in standards. MA plans lean on clinical criteria sets, tools like InterQual and MCG or proprietary algorithms, that don't always line up with the documentation conventions treating physicians actually use. A clinical note can fully support medical necessity under accepted standards of care and still get denied, simply because it lacks the specific keywords or structured data points the review algorithm is built to look for. A Congressional investigation found that denial rates at the three largest MA insurers, UnitedHealthcare, CVS/Aetna, and Humana, rose substantially after each expanded its use of AI-based authorization review. The U.S. Senate Permanent Subcommittee on Investigations went further, reporting that UnitedHealthcare's denial rate for post-acute care more than doubled during the exact stretch the company was rolling automation out across its review process. A class action, Estate of Lokken v. UnitedHealth Group, alleges that the company's AI tool, nH Predict, carried a very high error rate. A large share of the denials it generated were overturned on appeal, and a federal judge allowed part of that case to proceed in 2025.
The appeal numbers tell the real story here. More than four out of five MA prior authorization denials get overturned when a practice actually appeals them. The service was clinically appropriate all along. The denial was never functioning as a clinical safeguard. It was functioning as friction, a barrier built to suppress how much care gets delivered rather than to screen out care that wasn't warranted. For many independent practices, the staff time required to prepare and file an appeal costs more than the reimbursement at stake, so the appeal never gets filed, and the payer's financial incentive works exactly as designed.
CMS has now extended this same mechanism into traditional Medicare through a program called WISeR. WISeR launched January 1, 2026, with prior authorization applying to services delivered on or after January 15, 2026, and it runs through December 2031 across six states: Arizona, New Jersey, Ohio, Oklahoma, Texas, and Washington. Available evidence suggests that AI-aided prior authorization leads to higher denial rates and larger reductions in healthcare use than when insurers make prior authorization decisions without AI. Chronic Condition Special Needs Plans add another layer on top of all this. A C-SNP can require documentation that explicitly confirms the patient's qualifying chronic condition using that specific plan's coding criteria, so a general ICD-10 code that would clear standard review elsewhere can trigger a denial or an audit under a C-SNP.
Coding Errors and the ICD-10 Specificity Gap: Automatic, Unappealable Denials
Even a claim that clears prior authorization can still die at the coding stage, and the clearest example of why is the Multiple Sclerosis code change that took effect in 2025. The general code, G35, became invalid as of October 1, 2025. Providers now have to bill one of four subtype-specific codes: relapsing-remitting (G35.A), primary progressive (G35.B), secondary progressive (G35.C), or unspecified (G35.D), and they also have to specify whether the condition is active or non-active. Anyone who submits the old G35 code after that date gets an automatic denial with no appeal path available, because the code simply doesn't exist in the active set anymore.
A second version of the same trap appears in medical necessity review. Billing a Vitamin D screen, CPT code 82306, against a diagnosis of routine fatigue, R53.83, triggers a denial because that diagnosis code isn't on the approved list for that CPT code under the active Local Coverage Determination, even when the clinical reasoning behind the test is entirely sound. Laterality works the same way: failing to document whether limb or flank pain is on the right side, the left side, or both is a common and avoidable trigger for denial, because the code isn't specific enough for an automated system to pass it even when the clinical picture is correct. Research from HFMA chapters found that errors in diagnosis coding, modifier usage, and a lack of medical record support were the top three drivers of coding-related denials in 2025.
Medical necessity denials, coded CO-50, run on the same logic. A service only counts as medically necessary if it fits the diagnosis submitted, follows accepted standards of care, and has no cheaper alternative, and payer AI checks that definition against the codes sitting on the claim rather than against the full clinical note. Advanced imaging ordered without documented conservative treatment first, or a diagnostic test submitted without a clear indication in the code set, gets denied under CO-50 even when the treating physician's judgment was entirely defensible. The practical consequence of all this is that a coding team whose knowledge was validated against the 2024 or 2025 code set is already working from stale information wherever the 2026 updates touched their specialty.
How documentation gaps let payer AI systems deny claims that clinical notes support
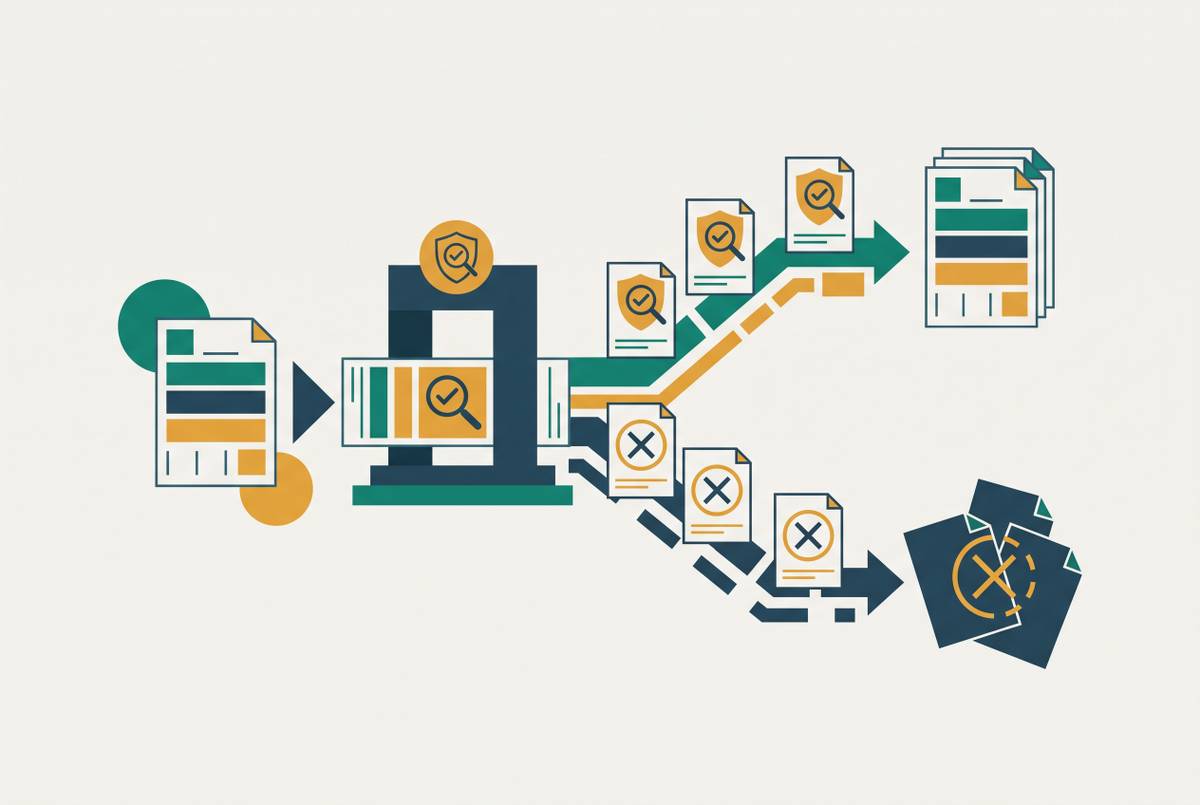
Payer AI systems read documentation in whatever format arrives on their end, not the format a physician actually wrote it in, and that gap between a clinician's narrative notes and what an automated reviewer can parse has turned into its own category of denial. Most practices now send records electronically, but unstructured clinical notes still often fail to reach the payer's AI reviewer in a form it can interpret. A CO-16 denial, coded as missing or incomplete documentation, results even when the physician's chart is thorough and complete.
Durable medical equipment claims are among the services most exposed to this failure mode, because the clinical justification for the equipment tends to live in narrative text that an automated system isn't built to extract. The chart can say everything a human reviewer would need to approve the claim, and still get rejected because the system reading it was never built to find that information in prose form. That distinction, between what a clinical note supports and what an automated reviewer can actually process, runs through every stage of the denial pattern described here: eligibility checks that never happen in real time, authorizations built on criteria sets that don't match clinical practice, codes that fall out of date faster than billing teams can track, and documentation that says the right thing in the wrong shape. Each failure point is specific, repeatable, and, in principle, fixable, which makes the current denial rate so frustrating.
Sources
- Top 10 Reasons Medicare Denies Claims in 2026 (And What to Do Next) | Understood Care
- Medicare Advantage Insurers Made Nearly 53 Million Prior Authorization Determinations in 2024 | KFF
- Medicare Advantage Denials Rise With Prior Authorizations
- The 2026 Medicare Advantage Shift: Why Denials Will Spike
- 4 in 10 Practices See Denials Above 10%