Prior Authorization Requirements by Specialty for Commercial Payers
Different specialties face vastly different prior auth burdens from payers.
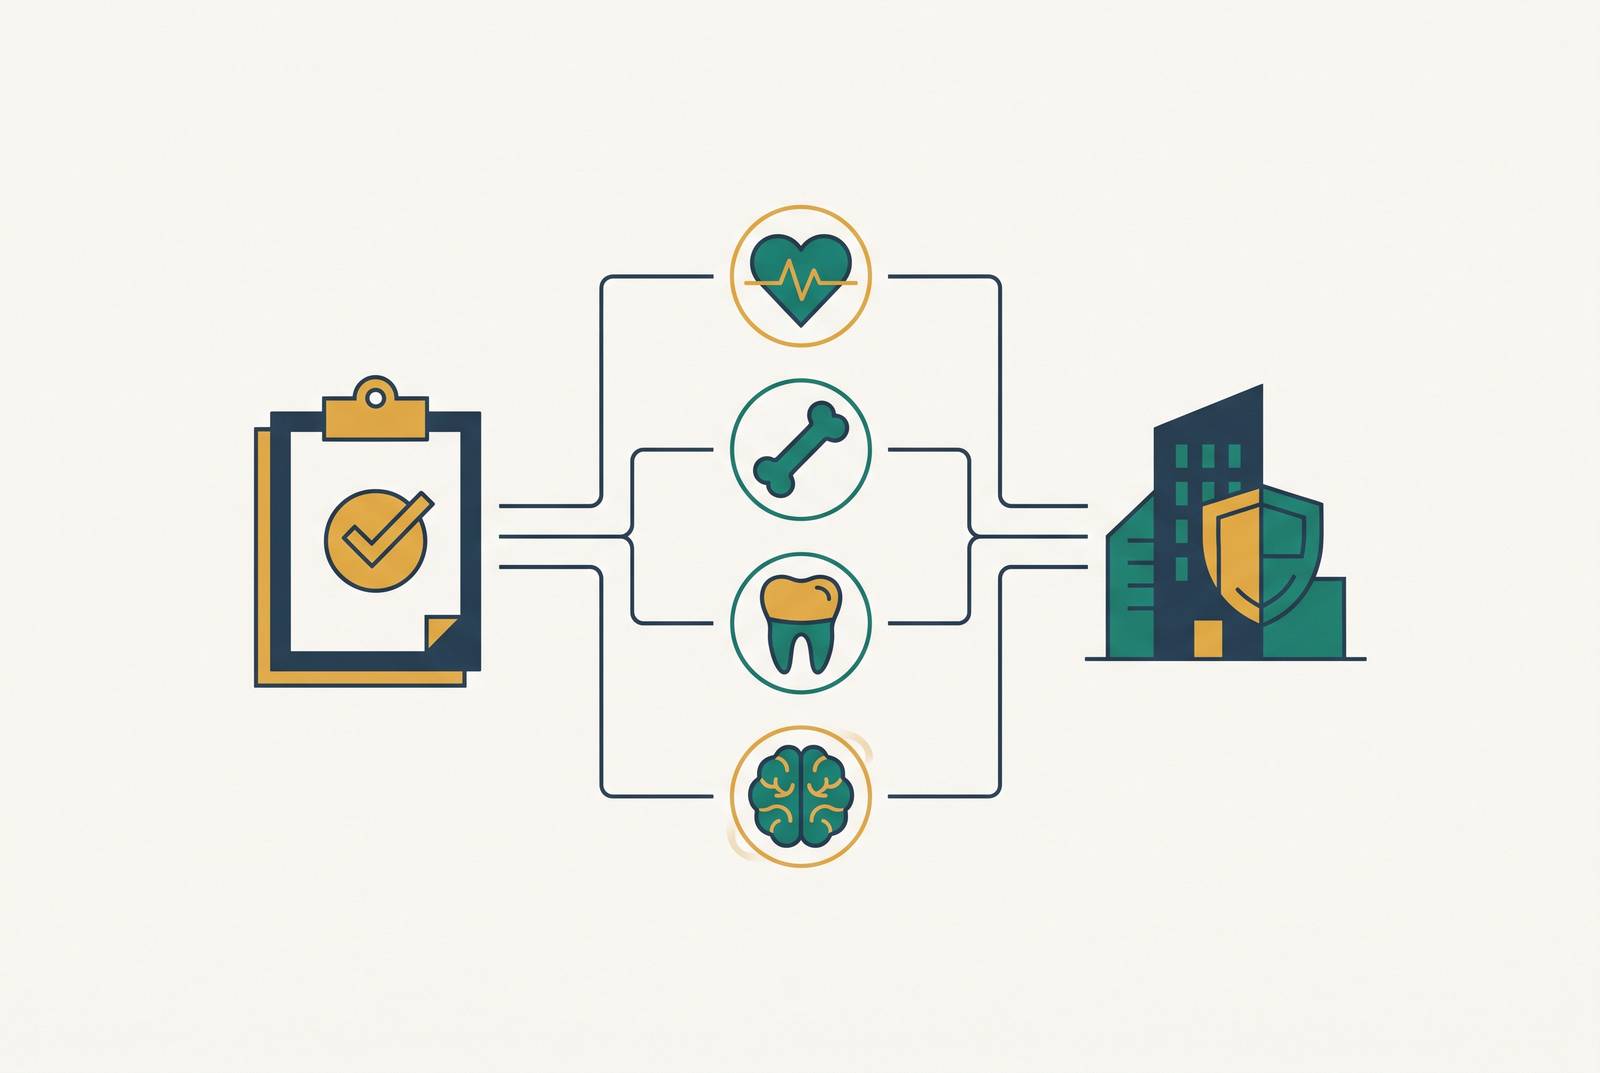
Prior authorization is not one problem. It's dozens of small, specialty-specific problems that happen to share a name, and treating them as a single administrative headache is exactly why so many practices manage the burden badly. A dermatologist and a radiation oncologist both fill out "prior auth" paperwork, but the volume, the denial risk, and the clinical stakes attached to each request look almost nothing alike. Understanding that variation, by specialty, by service type, and by payer, is the actual starting point for any practice trying to get ahead of the workload instead of just absorbing it.
Payers don't spread prior authorization evenly across medicine, and they never intended to. They aim it where they think utilization can be steered: high-cost imaging, specialty drugs, procedures with cheaper substitutes, and the gray-zone cases where medical necessity can't be settled just by reading the chart. That is the whole logic, requiring nothing further to complete it. It's why oncology, radiology, and a handful of surgical specialties carry far heavier prior auth loads than primary care or pediatrics ever will, and why comparing those loads as if they belong on the same scale misses the point entirely.
Rheumatology and gastroenterology land in a category of their own, and the reason is simple: biologics and specialty infusions. Those drug classes carry list prices steep enough that a payer's calculus almost always adds a review step before the first dose ships. Radiation oncology and diagnostic imaging get hit for a related but distinct reason. Advanced imaging and radiation therapy planning cost enough, and get substituted for cheaper alternatives often enough, that insurers built whole utilization management departments around reviewing them before they happen.
Orthopedics and pain management face a version of the same problem, except the driver is volume. Joint injections, spinal procedures, and durable medical equipment requests come through by the hundreds, and payers have stacked step-therapy rules and site-of-service requirements on top of the base authorization. A single case can trip two or three separate reviews before a patient ever gets treated. That stacking, not the base requirement itself, is what actually drains staff time in these departments.
The procedures that trigger mandatory review
Inside any one specialty, it's rarely everything that needs sign-off. It's a defined subset, and that subset follows a pattern across commercial payers even when the billing codes attached to it differ from plan to plan.
Advanced imaging is close to universal. MRI and CT scans ordered for non-emergent reasons almost always need prior authorization, no matter which commercial payer is on the hook. Specialty drugs given in-office, biologics and infused therapies especially, sit in the same bucket. Elective surgery, particularly spinal fusion, joint replacement, and bariatric surgery, routinely gets flagged for review, and so does durable medical equipment once it crosses a cost threshold that varies by payer but rarely by much. Genetic and molecular testing is the newest addition to most payer review lists, tracking the fact that both the volume and the price tag on those tests have climbed fast.
Emergency care is the one clean exception, and it should be stated directly rather than hedged around: federal and state rules bar payers from requiring prior authorization before emergency treatment, full stop. Most commercial plans write that exclusion directly into their utilization management policy rather than leaving it implied. The dividing line that falls out of this is blunt but real. Scheduled, elective, and high-cost services get the heavy review. Urgent and emergent care mostly skips it.
Where payer differences show up
Which services need prior auth is fairly consistent across the major commercial payers. How that requirement gets carried out is where the real differences show up, and that's where most of the administrative burden actually lives, not in the coverage rules themselves.
Turnaround time is the first fault line. Some plans commit to a decision within a few days on standard requests; others take noticeably longer, and the expedited or urgent pathways that exist come loaded with their own documentation demands, so speed gets traded for paperwork. Submission channels split the same way. Some payers still run parts of the process through fax and phone, full stop, while others have shifted to online portals or electronic prior authorization tools wired directly into a practice's records system. A practice under contract with four or five commercial payers can end up running four or five separate submission workflows for services that are, clinically, identical down to the code.
Documentation is the other place the gap opens up, costing the most staff hours. One payer's imaging policy might accept a referring physician's note as enough to justify the scan. Another might demand a full clinical criteria questionnaire, built around its own internal utilization framework, where leaving a single field blank is enough to trigger a denial. Orthopedics and oncology, the two specialties dealing with the largest number of payers day to day, end up building internal reference sheets just to track which payer wants which form for which code, because no vendor or clearinghouse has solved that mapping problem for them.
The operational takeaway
None of this variation is random, even on the tenth authorization request of a Tuesday morning when it feels that way to whoever's filing it. It follows the cost and utilization logic each payer applies to each service line, and that logic can be mapped in advance, which is exactly what most practices fail to do.
Practices that build specialty-specific playbooks, tracking which codes trigger review, which payer wants which form, and where an expedited pathway actually exists, turn an unpredictable cost center into a mappable one. Treating every request as a one-off, by contrast, is the choice that turns prior authorization into the single biggest drag on staff time and cash flow most practices report today. That second path is the default only because nobody built the map. It's not inevitable, and it's not a fair trade for the alternative.